
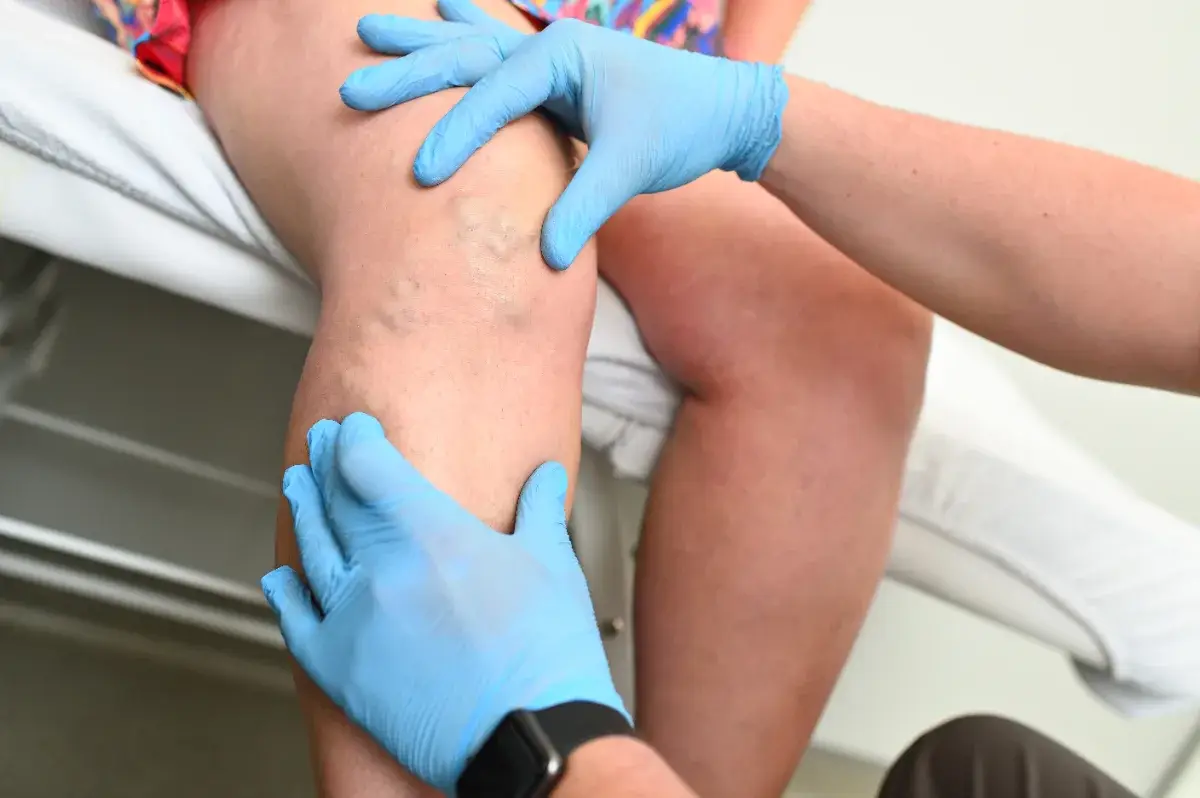
Can varicose veins be treated without surgery? Many people ask this, and the honest answer has two parts. There are minimally invasive treatments, and there are supportive steps like compression stockings, leg elevation, and walking. But no option can promise your veins will never be a problem again, because new vein problems can still develop over time.
Which option fits you depends on your symptoms, your ultrasound findings, and your goals. This article explains the choices in plain English so you know what to ask about.
At VidaVascular, a vascular and interventional care practice, vein care starts with understanding why your legs feel the way they do. Treatment is then matched to that reason.
What does treatment realistically mean for varicose veins?
Your leg veins have tiny one-way valves that help push blood upward against gravity. When valves weaken, blood can fall backward and pool in the vein, which is called venous reflux. Over time, the vein stretches and becomes varicose.
Treatment aims at the reason for your symptoms, not just at how the veins look. A good plan usually considers your symptoms, ultrasound findings, and goals. It also stays honest about the fact that new vein problems can still develop later.
What supportive steps might be recommended?
Depending on your case, a clinician may suggest supportive steps. These can be used as alternatives or as add-ons to other treatments:
- Compression stockings
- Leg elevation
- Walking
- Weight management, when relevant
These steps are not a one-size-fits-all plan. If you have venous leg ulcers, studies show that treating superficial reflux earlier can help ulcer healing, alongside compression.
What is endovenous ablation?
Endovenous ablation is a minimally invasive treatment used to close a refluxing vein from the inside. “Endovenous” means inside the vein, and “ablation” means using energy to seal it closed. The most common types are radiofrequency ablation and endovenous laser ablation.
Think of a refluxing vein as a leaky pipe. Ablation closes that faulty segment, and blood re-routes into healthier veins. Many patients feel less heaviness, aching, and swelling over time.
Research and guidelines support endovenous ablation as a first-line treatment for many patients with symptomatic saphenous vein reflux, often with faster recovery than older surgical stripping approaches. It is typically done without large incisions, and many patients report symptom improvement, including better quality of life.
It is widely used, but it is not for everyone, and it is not the only tool available. You can read more on our varicose veins and endovenous ablation page.
What about sclerotherapy and other options?
Sclerotherapy means injecting medication to close smaller veins. The medicine irritates the inside lining of the vein, which helps the vein close and fade over time as your body reabsorbs it. Ultrasound-guided foam sclerotherapy may be used for certain vein patterns.
Two sclerosants, the medicines used for injection, are commonly discussed in major guidelines and studies: polidocanol and sodium tetradecyl sulfate. In a randomized, double-blind clinical trial, both were compared with placebo for spider and reticular veins, supporting sclerotherapy as an established approach with measurable improvement.
Results build gradually. People often see fading over weeks, and more than one session is often needed for cosmetic blending. Spider veins usually improve but do not always disappear in one session, and new ones can develop later. We cover this in more detail on our spider veins and sclerotherapy page.
Another option that may be recommended is phlebectomy, which removes bulging surface veins through tiny punctures. Your clinician can explain whether it, or a combination of approaches, suits your vein pattern.
Different treatments, including laser and injection approaches, vary in how well they clear small veins and in their side effects. That is why some patients do best with combination planning.
What are the risks and side effects?
Every treatment has trade-offs. For endovenous ablation, possible risks and side effects include:
- Bruising or soreness along the treated vein
- Temporary numbness or tingling near the skin, since nerve irritation can happen, especially below the knee
- Inflammation of a superficial vein (phlebitis)
- Skin burns, which are rare and more associated with laser
- Blood clots, a risk that is low but not zero
For sclerotherapy, common temporary side effects include bruising or tenderness, temporary darkening of the skin (hyperpigmentation), tiny new blush vessels near the treated area, and small lumps or firmness that soften over time. Hyperpigmentation is a known side effect, and longer-lasting pigmentation can occur in a smaller subset of people.
When should you see a vascular specialist?
If you have aching, heaviness, swelling, skin changes near the ankle, or a vein that is tender and cord-like, it is worth getting checked. Most vein evaluations start with a conversation about your symptoms and a physical exam. A duplex ultrasound, a painless test that shows blood flow and checks for reflux, is often the key test.
That information helps match a treatment plan to the cause of your symptoms. To learn how VidaVascular approaches this, see our varicose vein treatment page.
Know the emergency signs. If you ever have sudden one-leg swelling, chest pain, or shortness of breath, that can be an emergency because it may involve a blood clot. Call 911 or seek emergency care right away.
Ready to talk through your leg symptoms? Call VidaVascular at (866) 800-2346 or request an appointment. You can be seen at our offices in Oxon Hill, MD, White Plains, MD, and Springfield, VA (see all locations). We accept most major insurance providers, so please call to confirm your plan.
References
- Brittenden, J., Cotton, S. C., Elders, A., Ramsay, C. R., Norrie, J., Burr, J. M., Campbell, B., & Lee, A. J. (2014). A randomized trial of treatments for varicose veins. The New England Journal of Medicine, 371(13), 1218-1227.
- Gloviczki, P., Comerota, A. J., Dalsing, M. C., Eklof, B. G., Gillespie, D. L., Gloviczki, M. L., Lohr, J. M., McLafferty, R. B., Meissner, M. H., Murad, M. H., Padberg, F. T., Pappas, P. J., Passman, M. A., Raffetto, J. D., & Wakefield, T. W. (2011). The care of patients with varicose veins and associated chronic venous diseases: Clinical practice guidelines of the Society for Vascular Surgery and the American Venous Forum. Journal of Vascular Surgery, 53(5 Suppl), 2S-48S.
- Gohel, M. S., Heatley, F., Liu, X., Bradbury, A., Bulbulia, R., Cullum, N., … & EVRA Trial Investigators. (2018). A randomized trial of early endovenous ablation in venous ulceration. The New England Journal of Medicine, 378(22), 2105-2114.
- Rasmussen, L. H., Lawaetz, M., Bjoern, L., Vennits, B., Blemings, A., & Eklof, B. (2011). Randomized clinical trial comparing endovenous laser ablation, radiofrequency ablation, foam sclerotherapy, and surgical stripping for great saphenous varicose veins. British Journal of Surgery, 98(8), 1079-1087.
- van den Bos, R. R., Arends, L., Kockaert, M., Neumann, M., & Nijsten, T. (2009). Endovenous therapies of lower extremity varicosities: A meta-analysis. Journal of Vascular Surgery, 49(1), 230-239.
- Wittens, C., Davies, A. H., Baekgaard, N., Broholm, R., Cavezzi, A., Chastanet, S., … & De Maeseneer, M. (2015). Editor’s Choice: Management of chronic venous disease: Clinical practice guidelines of the European Society for Vascular Surgery (ESVS). European Journal of Vascular and Endovascular Surgery, 49(6), 678-737.
- Nakano, L. C. U., Cacione, D. G., Baptista-Silva, J. C. C., & Flumignan, R. L. G. (2021). Treatment for telangiectasias and reticular veins. Cochrane Database of Systematic Reviews, 2021(10), CD012723. https://doi.org/10.1002/14651858.CD012723.pub2
- Rabe, E., Schliephake, D., Otto, J., Breu, F. X., & Pannier, F. (2010). Sclerotherapy of telangiectases and reticular veins: A double-blind, randomized, comparative clinical trial of polidocanol, sodium tetradecyl sulphate and isotonic saline (EASI study). Phlebology, 25(3), 124-131. https://doi.org/10.1258/phleb.2009.009043
- Rabe, E., Pannier, F., & Guideline Group. (2014). European guidelines for sclerotherapy in chronic venous disorders. Phlebology, 29(6), 338-354. https://doi.org/10.1177/0268355513483280
- Bossart, S., Daneluzzi, C., Cazzaniga, S., Ramelet, A. A., Uthoff, H., Seyed Jafari, S. M., et al. (2023). Skin hyperpigmentation after sclerotherapy with polidocanol: A systematic review. Journal of the European Academy of Dermatology and Venereology, 37(2), 274-283. https://doi.org/10.1111/jdv.18639
- Bontinis, V., Bontinis, A., Koutsoumpelis, A., Claridge, M., Chorti, A., Rafailidis, V., et al. (2023). Interventions for the treatment of lower limb telangiectasias and reticular veins: A systematic review and network meta-analysis. European Journal of Vascular and Endovascular Surgery, 66(4), 560-576. https://doi.org/10.1016/j.ejvs.2023.05.029



